
Bespoke Architecture and Longevity
Bespoke Architecture and Longevity examines how housing and neighbourhood conditions relate to health and everyday life. The review brings published research into an architectural discussion of air, light, movement, comfort and access to outdoor space. Its purpose is to inform the design brief and identify questions for evaluation. It is not a clinical study, and it does not establish that a particular building extends lifespan or changes gene activity.

Is Longevity Determined by Genetics?
Health and lifespan reflect many interacting conditions, including inherited traits, living conditions, behaviour and access to care. For architects, the useful question concerns the conditions that a building can help improve. Housing quality, access, ventilation and the surrounding public realm can be considered alongside residents’ needs without treating design as a substitute for healthcare.
The studies cited here examine different populations, places and outcomes. An association that remains after statistical adjustment is relevant evidence, but it does not automatically establish causation. Income, access to services, residential selection and other factors can be difficult to separate from the physical characteristics of a neighbourhood. These limits matter when translating population research into a design decision.
The Demography of the World Population from 1950 to 2100
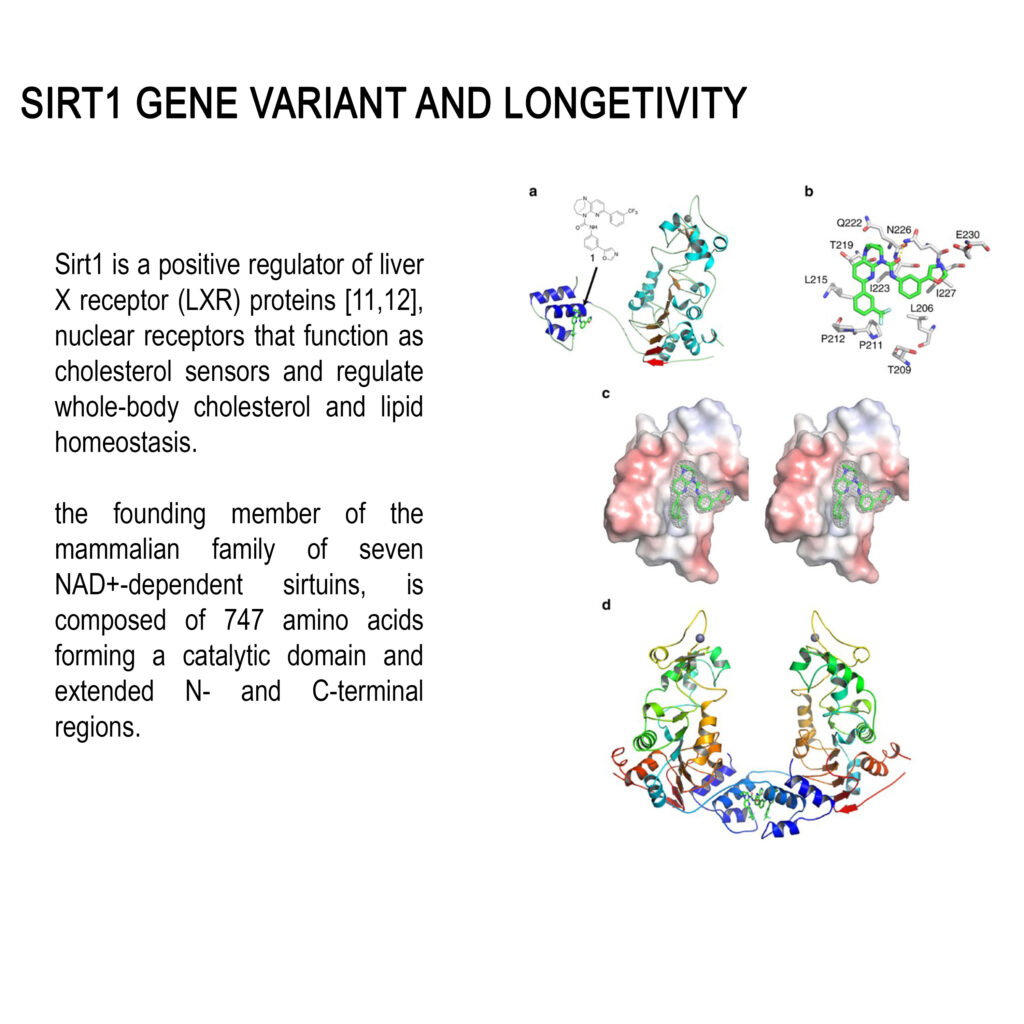
Population pyramids show the changing age structure of a population. Fertility, mortality and migration all affect their shape. The accompanying historical and projected chart provides demographic context for the research; it should not be read as a measurement of the effect of architecture on lifespan.
Wight and colleagues (2010) examined neighbourhood context and mortality among older urban adults. Their study is relevant to the wider relationship between place, social resources and health. It does not isolate the effect of an architectural style or demonstrate that a more expensive home produces a longer life.
The Sirt1 Gene and the Environmental Interface

The original presentation introduces SIRT1 as a biological reference within the discussion of ageing. The architectural research does not measure SIRT1 activity or test a mechanism connecting a room design with gene expression. The illustration is retained as part of the research archive, with that distinction made explicit.
The design questions remain at the scale of occupation: whether a bedroom can be darkened, whether unwanted noise can be controlled, whether daily routes are accessible, and whether residents have comfortable places to rest and move. These questions can guide a brief and later evaluation without making a molecular claim about the building.
Air, Sleep, and Movement
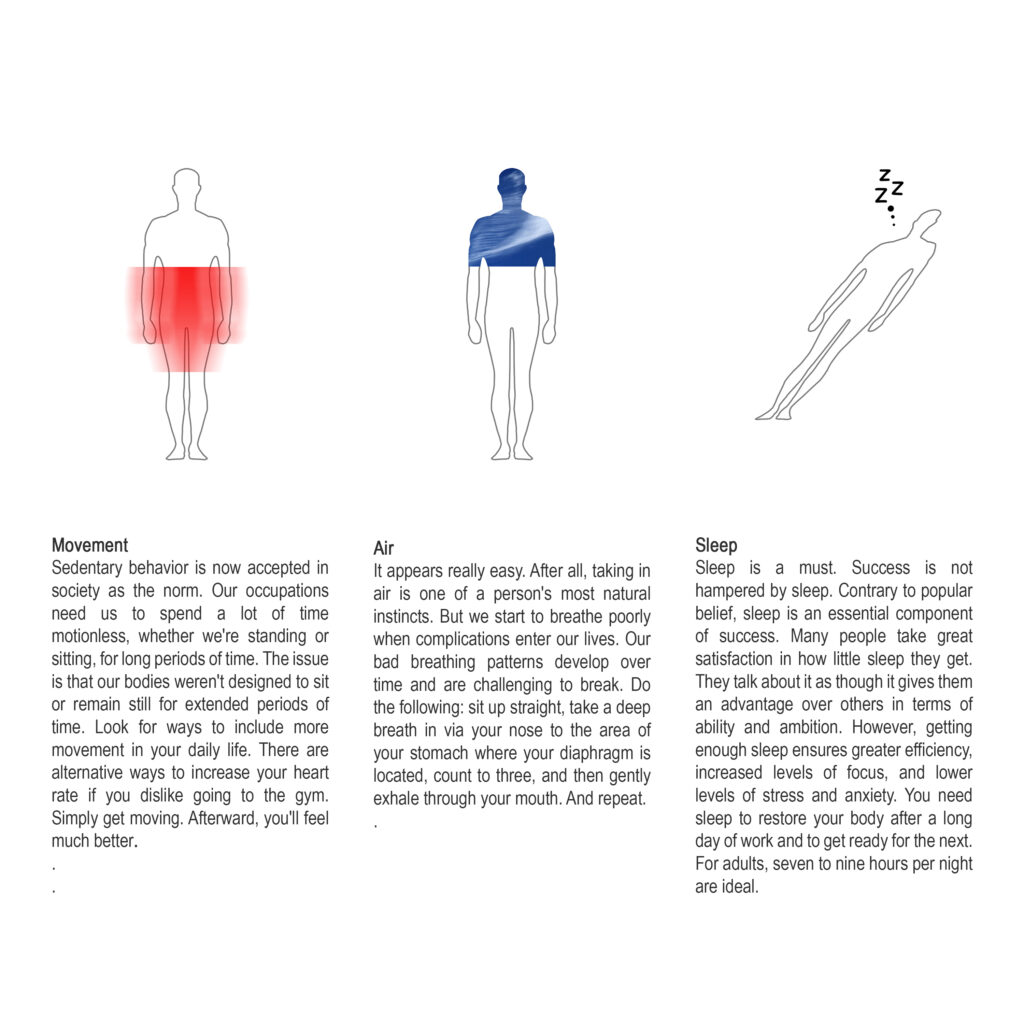

Air, sleep and movement provide three practical starting points for an architectural brief. Ventilation, pollutant sources, crowding and the local outdoor environment need to be considered together. Pratama and colleagues (2022) studied built-environment conditions and respiratory infection symptoms in Indonesia. Their findings are specific to that study and should not be converted into a general recommendation for urban sprawl or a guarantee about an individual building.
At room scale, the design team can specify acoustic separation, controllable light and suitable thermal conditions. At building scale, it can make stairs legible, provide accessible alternatives and connect rooms with useful outdoor spaces. The quality of these provisions should be assessed in use, taking account of different ages, abilities and routines.
Greenspace, Greenness, and the Architecture of Longevity
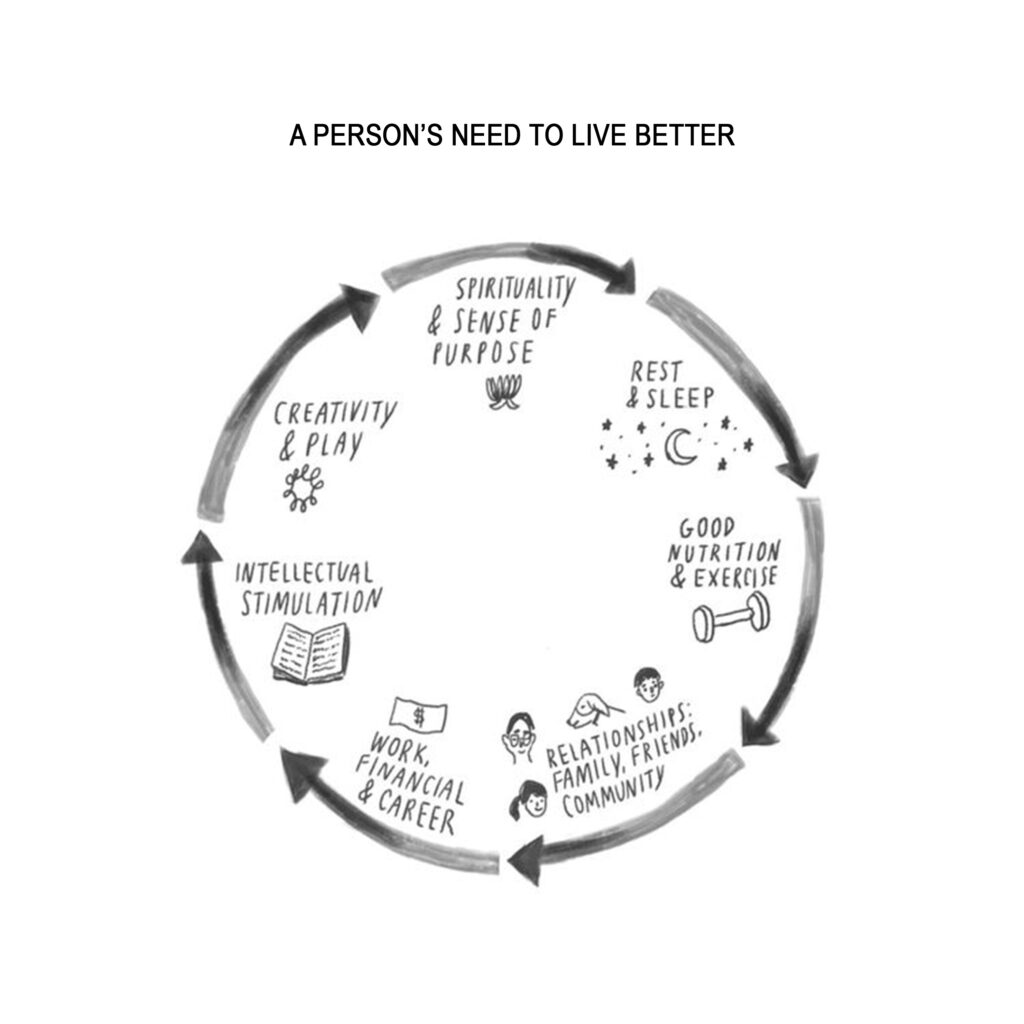
A systematic review by Sarkar, Dong and Webster (2023) reported associations between several built-environment attributes and cardiovascular outcomes. Greenness and walkability were among the attributes examined. The review also identified limitations in study design and confounding. It supports further investigation of these relationships rather than a promise that adding vegetation to any project will produce a particular health result.
South, Kondo and Branas (2023) examined greenspace and mortality inequalities in Philadelphia. Their work raises a question of access as well as quantity. In an architectural brief, a planted area should be considered in relation to the people who can reach and use it, its shade, maintenance and connection to daily routes. Findings from one city should not be transferred directly to a different population or climate.
Architecture, Physical Activity, and Cardiovascular Risk

Howell and colleagues (2019) examined neighbourhood walkability and predicted cardiovascular risk in Ontario. For planning, the relevant questions include connections between streets, proximity to destinations and the practical conditions for walking. A risk estimate from that study is not a measured outcome for an INJ Architects project.
Within a building, the placement of stairs, courtyards and shared facilities can make everyday movement easier to incorporate into a routine. Routes also need shade, rest points, accessibility and clear orientation. The aim is to provide usable choices, with the effect on occupants assessed rather than assumed.
Urban Planning and the Quality and Length of Life

Xiao and colleagues (2018) studied changes in neighbourhood socioeconomic deprivation and subsequent mortality in a large US cohort. The findings concern neighbourhood conditions over time, not a controlled test of a design intervention. They help frame the relationship between place and health while leaving the contribution of particular architectural measures unresolved.

Pedestrian routes, cycling connections and access to everyday services bring the discussion into planning practice. Their usefulness depends on continuity, safety, climate and the ability of different residents to use them. The building brief and the wider neighbourhood should therefore be considered together.
Architecture: Need or Luxury?


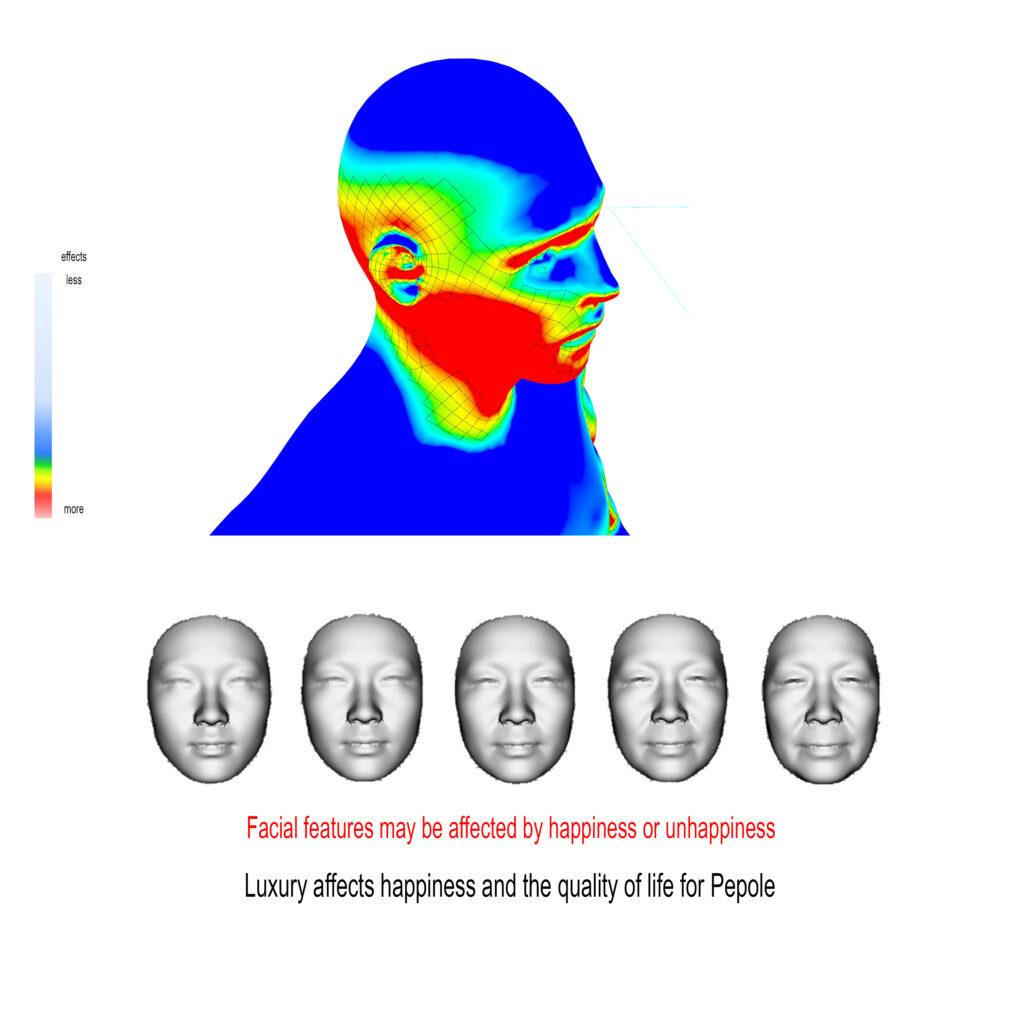
A high purchase price is not a health specification. Comparisons between expensive and less expensive homes also reflect differences in income, location, services and the people able to live there. The studies cited in this review do not establish that luxury architecture, as a category, extends life.
The architectural task is to define the qualities that residents need: enough usable space, manageable noise, suitable temperatures, access and reliable building services. These requirements can be written into a brief and evaluated after occupation. Their value is clearer when described directly than when treated as a general promise of luxury.
Urban Interventions and Effects

Public-space design brings several needs together: movement, rest, visibility, maintenance and social use. A well-positioned bench, a shaded route or an accessible entrance can help a space serve its users. None of these features works independently of management, surrounding uses and the daily conditions of the place.
Zhang and colleagues (2025) examined residential greenspace and wellbeing among older adults in different housing-price communities. Their study encourages attention to differences between users and neighbourhoods. For a project brief, this means asking who relies on the shared outdoor space, how it is reached and what activities it can realistically support.
Colors and Quality and Length of Life

Colour affects the appearance and legibility of a room, and its interpretation varies with lighting, material, culture and personal preference. A colour scheme should be tested in its actual setting. This review does not establish that a particular hue lowers cortisol, changes heart rate or extends lifespan.
Useful design questions include contrast at steps and doors, glare, the visibility of controls and the relationship between finishes under daylight and artificial light. Samples and mock-ups can support these decisions. Colour is part of the experience of a space, but it should not be presented as equivalent to a ventilation or medical intervention.
How Does the Quality of Materials Affect Us?

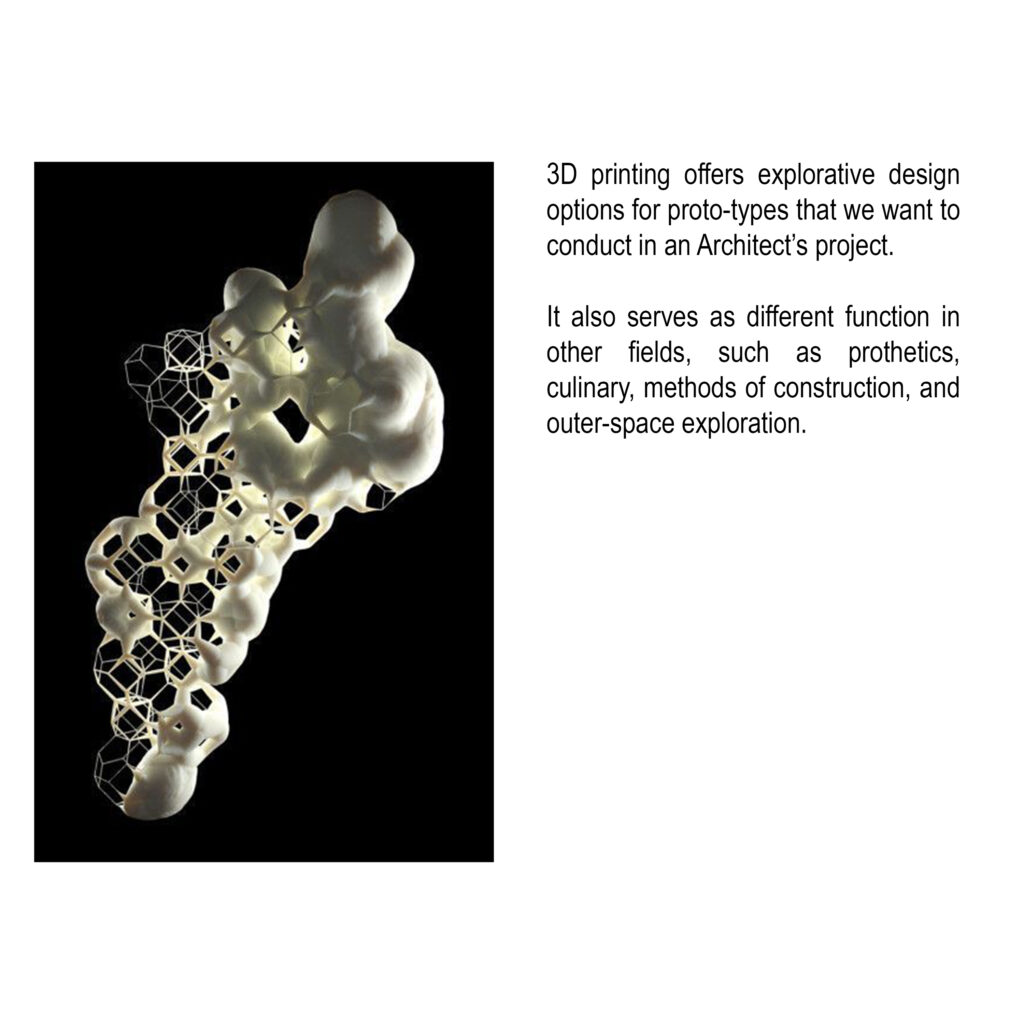
Material selection should consider emissions, finishes, cleaning, moisture and the conditions of installation. The label “natural” does not establish that a material is harmless, just as “synthetic” does not establish that it is unsuitable. Product-specific information and the complete assembly are needed. The WHO Housing and health guidelines provide a broader reference for housing-related risks and the coordination of health considerations in design.
Surfaces also shape everyday use through texture, grip, temperature and ease of maintenance. Handrails, handles and floors deserve attention at the scale of contact with the body. These are concrete specification questions. Claims about neurological effects or a universal emotional response require evidence beyond a material preference.

The presentation includes mountain settings as a reference for environmental experience. Altitude should not be treated as a model that an architect can reproduce through a room layout. Similarly, mechanical cooling is not inherently opposed to healthy occupation. Its design, control and maintenance must be considered alongside outdoor conditions, particularly in hot climates.

Wister (2005) discusses pathways through which the built environment may support or undermine health. For architectural practice, that discussion connects spatial design with accessibility, comfort, maintenance and social use. It supports collaboration with public-health and engineering specialists while keeping the responsibilities of each discipline clear.

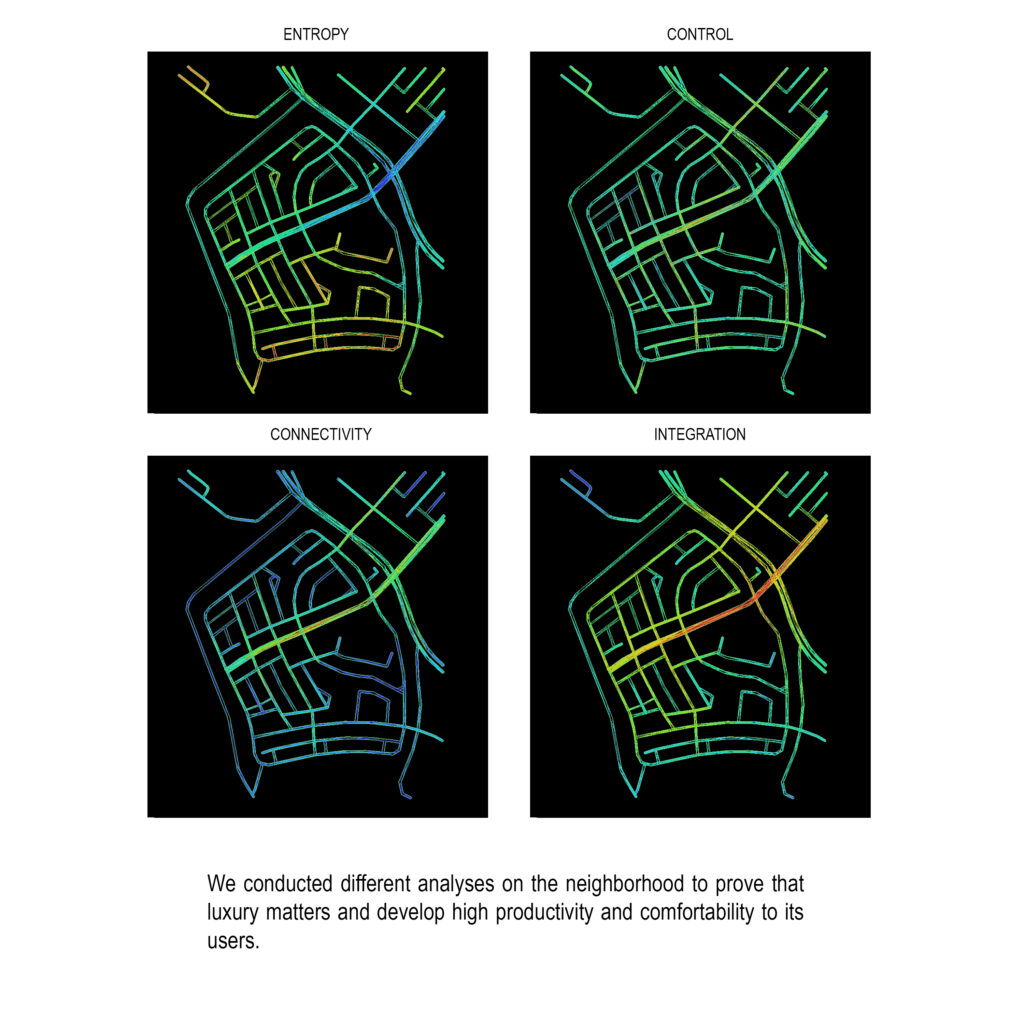
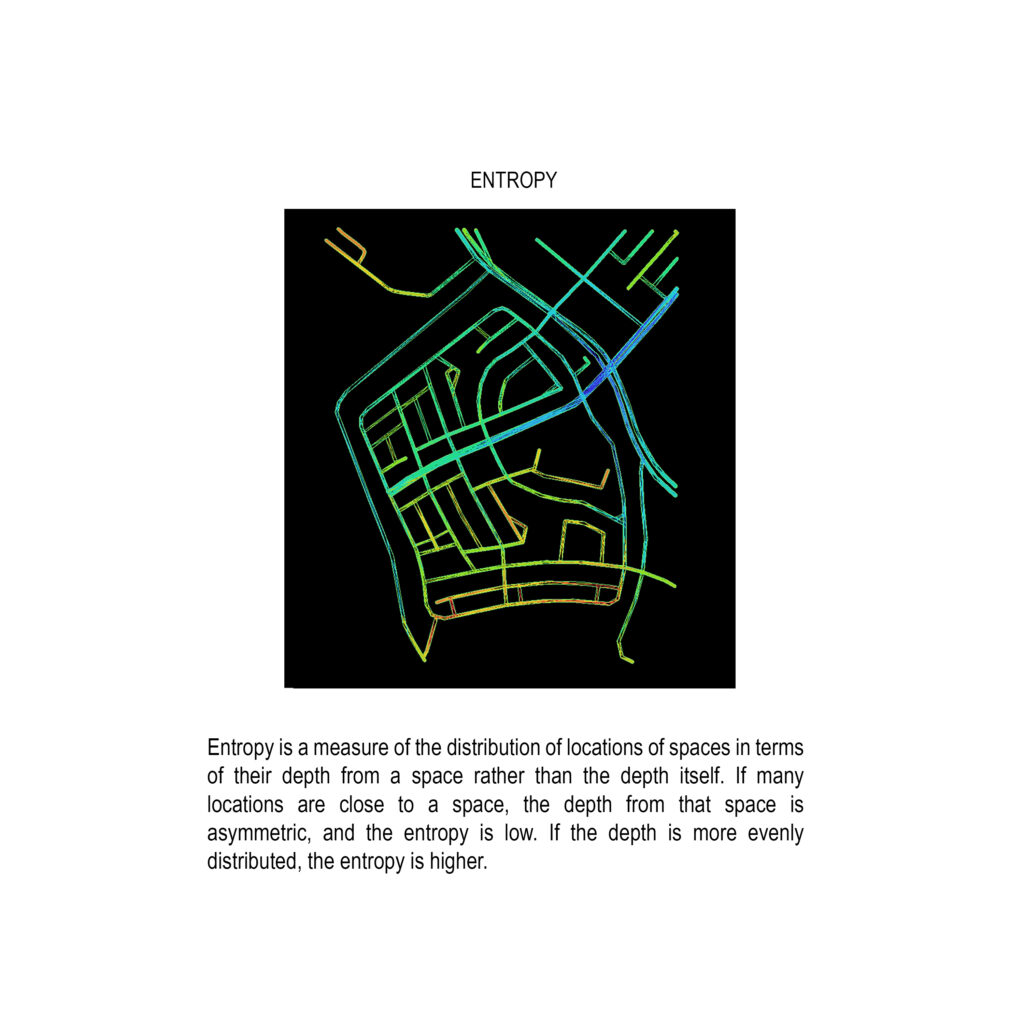
Dhahran appears in the original presentation as an urban reference. A city’s economic profile alone cannot demonstrate that its architecture causes higher productivity or longer life. The reference is retained as part of the study’s context, without using income figures as proof of a design effect.



Conclusion
The review identifies a set of architectural questions worth carrying into a project: how people reach their homes, how rooms support rest and movement, how building services perform, and how shared spaces are used. Published health research can help formulate these questions, provided its methods and limitations remain visible.
The next step is to turn the discussion into a brief with assessable requirements and a plan for evaluation after occupation. This could include comfort, access, maintenance and patterns of use. Such evidence would describe the performance of a particular building. It would still need to be distinguished from a claim about lifespan or biological causation.
References
- Pratama, A. P., Yudhistira, M. H., & Koomen, E. (2022). The relationship between the built environment and respiratory health: Evidence from a longitudinal study in Indonesia. SSM, Population Health, 19, 101193. https://doi.org/10.1016/j.ssmph.2022.101193
- Sarkar, C., Dong, J., & Webster, C. (2023). Associations of Urban Built Environment with Cardiovascular Risks and Mortality: A Systematic Review. Journal of Urban Health, 100, 1133–1154. https://doi.org/10.1007/s11524-023-00764-5
- Wister, A. V. (2005). The Built Environment, Health, and Longevity: Multi-Level Salutogenic and Pathogenic Pathways. Journal of Housing For the Elderly, 19(2), 49–70. https://doi.org/10.1300/j081v19n02_04
- Wight, R. G., Cummings, J. R., Karlamangla, A. S., & Aneshensel, C. S. (2010). Urban Neighborhood Context and Mortality in Late Life. Journal of Aging and Health, 22(2), 197–218. https://doi.org/10.1177/0898264309355980
- South, E. C., Kondo, M. C., & Branas, C. C. (2023). Does Urban Greenspace Reduce Mortality Inequalities Based on Poverty, Race, or Both in Philadelphia, PA? Journal of Urban Health, 100, 1155–1168. https://doi.org/10.1007/s11524-023-00748-5
- Xiao, Q., Berrigan, D., & Matthews, C. E. (2018). Ten-Year Change in Neighborhood Socioeconomic Deprivation and Rates of Total, Cardiovascular Disease, and Cancer Mortality in Older US Adults. American Journal of Epidemiology, 187(12), 2642–2650. https://doi.org/10.1093/aje/kwy181
- Howell, N. A., Tu, J. V., Moineddin, R., Chu, A., & Booth, G. L. (2019). Association Between Neighborhood Walkability and Predicted 10-Year Cardiovascular Disease Risk: The CANHEART Cohort. Journal of the American Heart Association, 8(21), e013146. https://doi.org/10.1161/jaha.119.013146
- Aliu, I. R., & Adebayo, A. (2013). Establishing a Nexus Between Residential Quality and Health Risk: An Exploratory Analytical Approach. Indoor and Built Environment, 22(6), 852–863. https://doi.org/10.1177/1420326×12447613
- Chen, B. (2023). Coincided disparity between housing price and health outcome. The Lancet Regional Health, Europe, 27, 100593. https://doi.org/10.1016/j.lanepe.2023.100593
- Zhang, Y., Zhang, T., & Rhodes, R. E. (2025). Unraveling the heterogeneity of pathways linking residential green space quantity and quality to the well-being of older adults in different housing price communities. Cities, 156, 105561. https://doi.org/10.1016/j.cities.2024.105561
The design principles that govern the application of this evidence base at INJ Architects are developed further in How We Work. The theoretical framework connecting human biological identity to architectural expression is documented in Archigenetics. For clients seeking residential or institutional commissions where the health performance of the built environment is treated as a primary design brief, the engagement framework is outlined in Bespoke Architecture. Related project: AC Water Sustainability.